

This is a sensitive topic and is presented for medical educational purposes for the general public to be aware of the cancers that can affect different parts of the human body – even the sensitive ones. Understandably, some people may be uncomfortable for cultural reasons, but this is one of the reasons why cancer incidence rates exist in many parts of the world. Here, in this section, there will be images for educational purposes. If you don’t want to read more about this, that’s understandable.
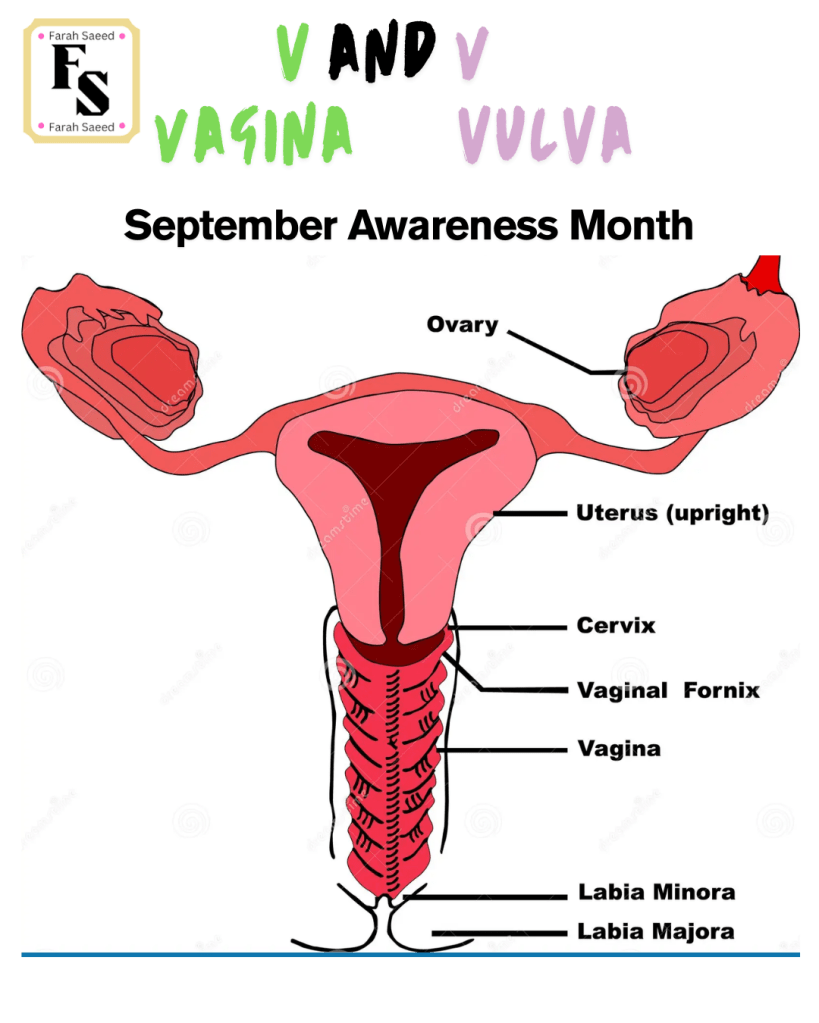
Objectives
Our posters have seven key objectives:
- To know what a gynaecological cancer is.
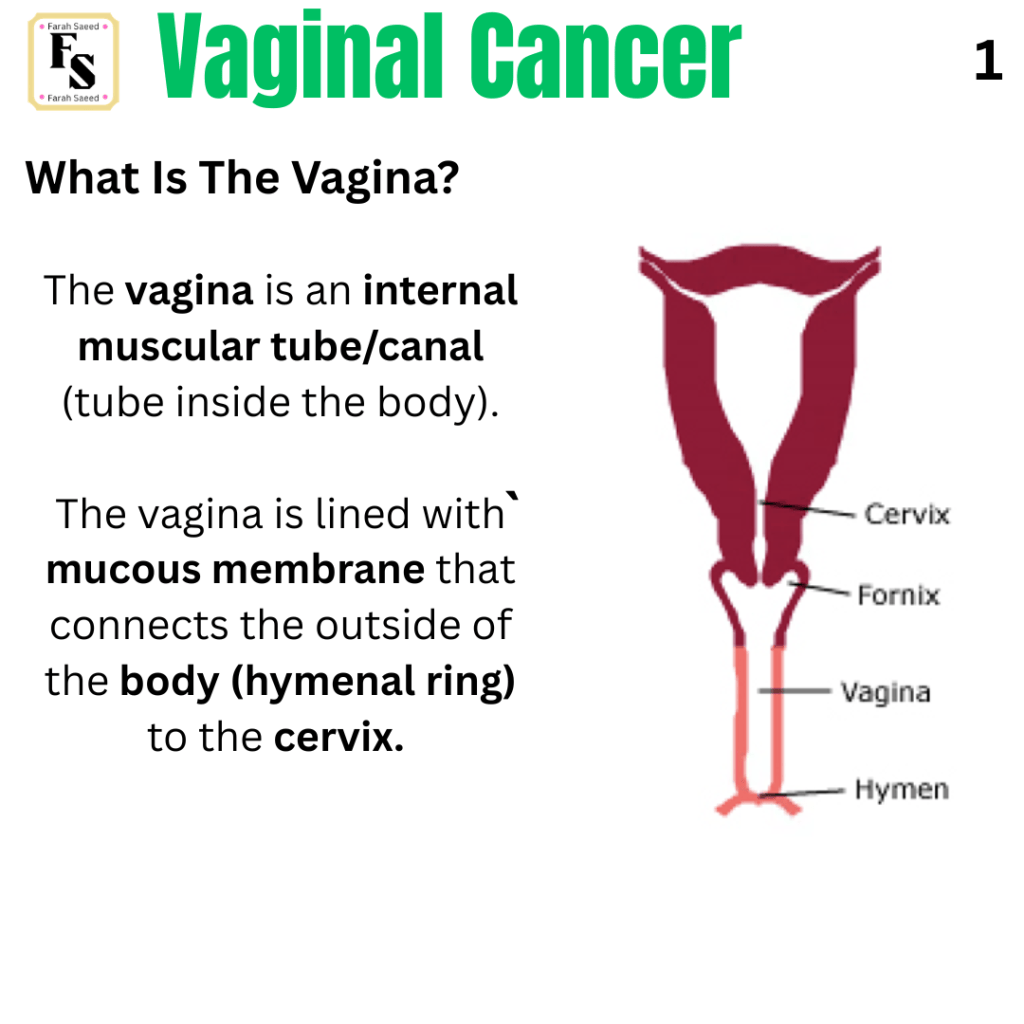
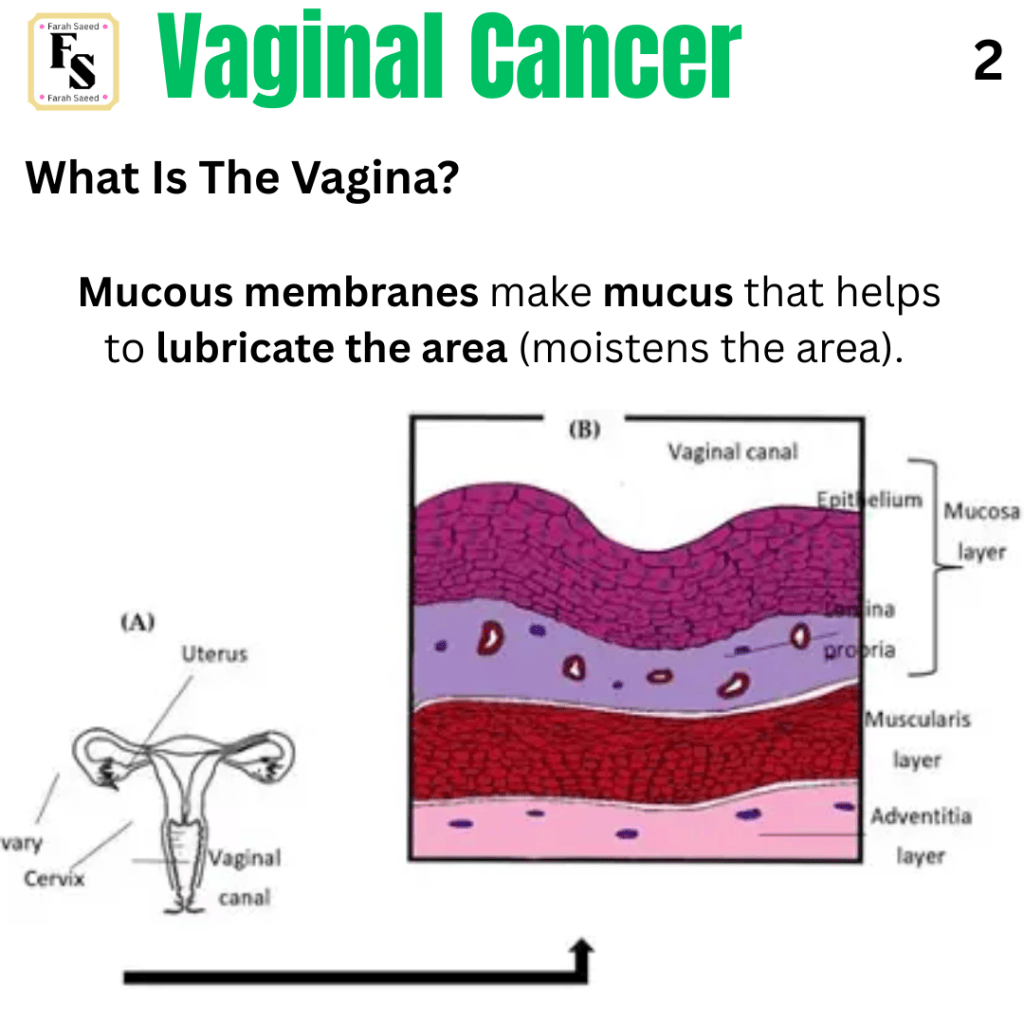
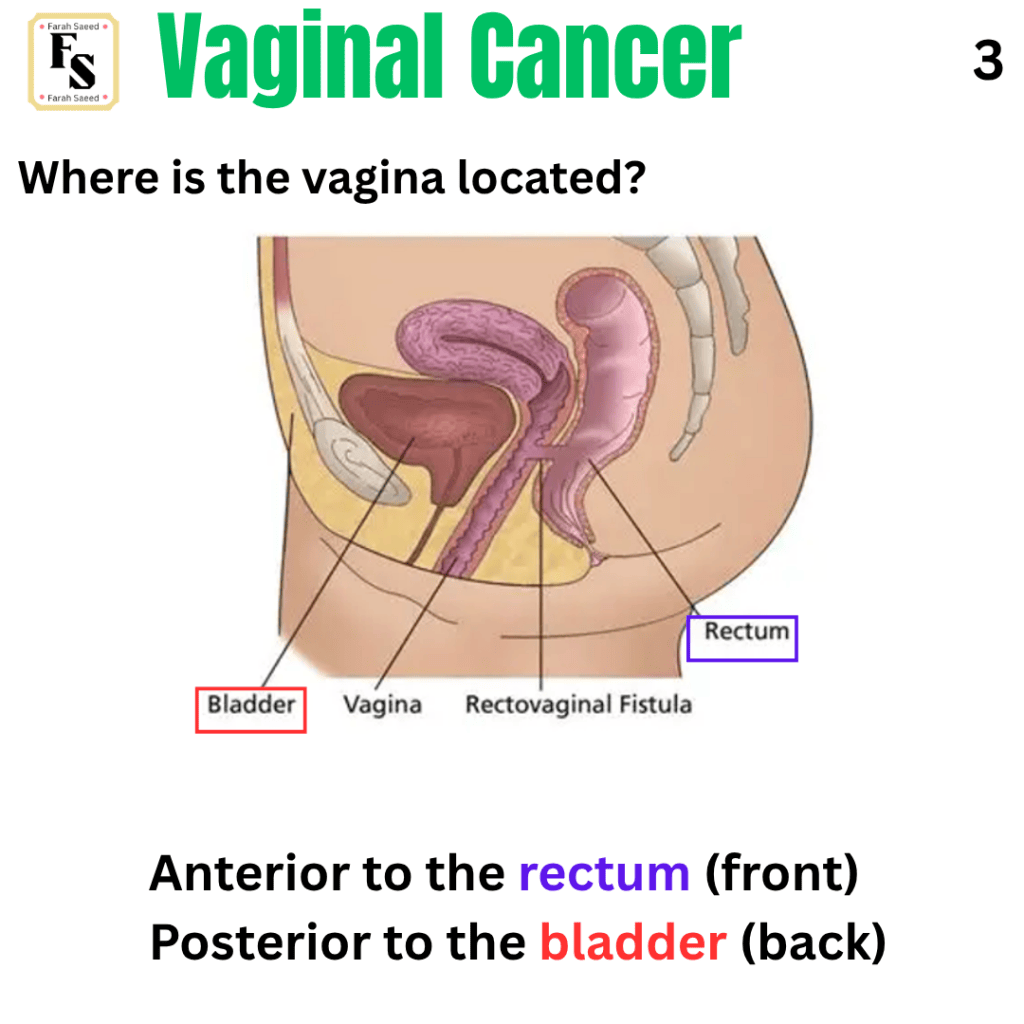
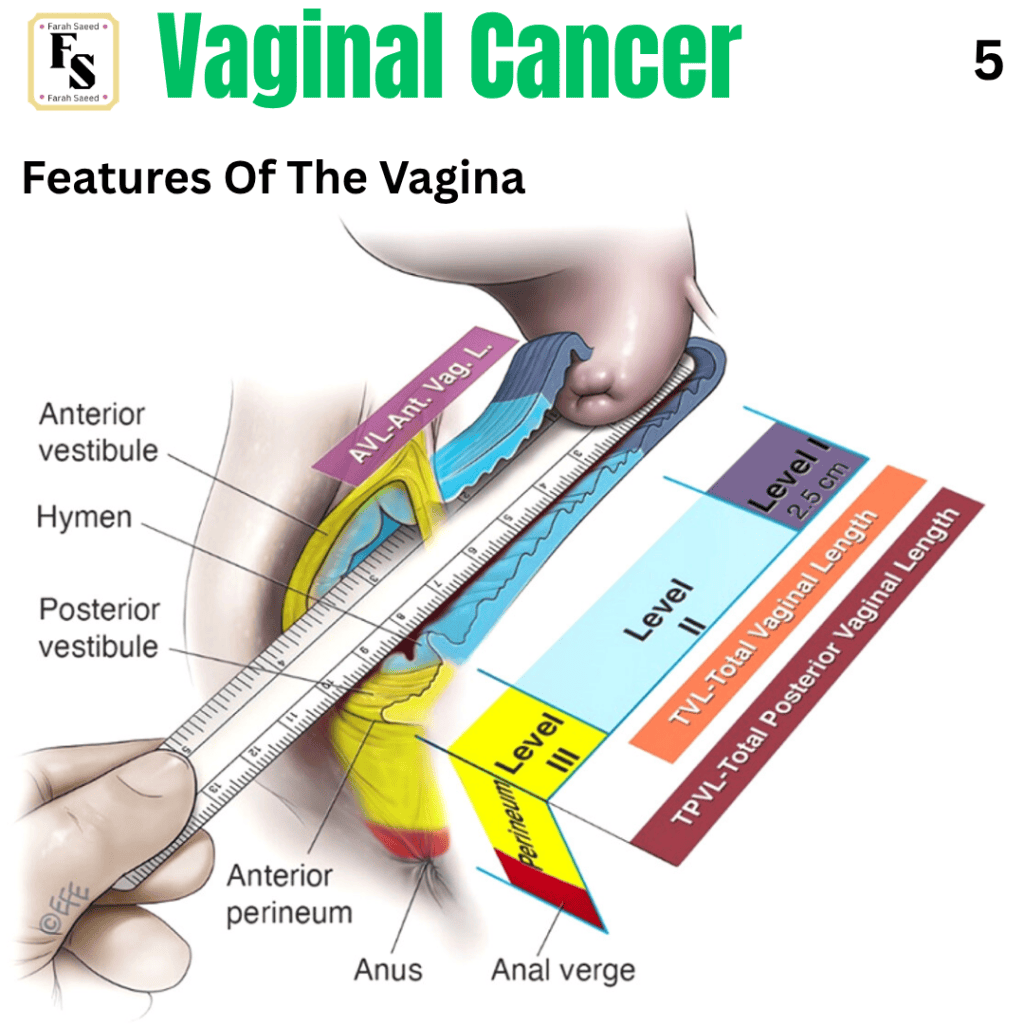
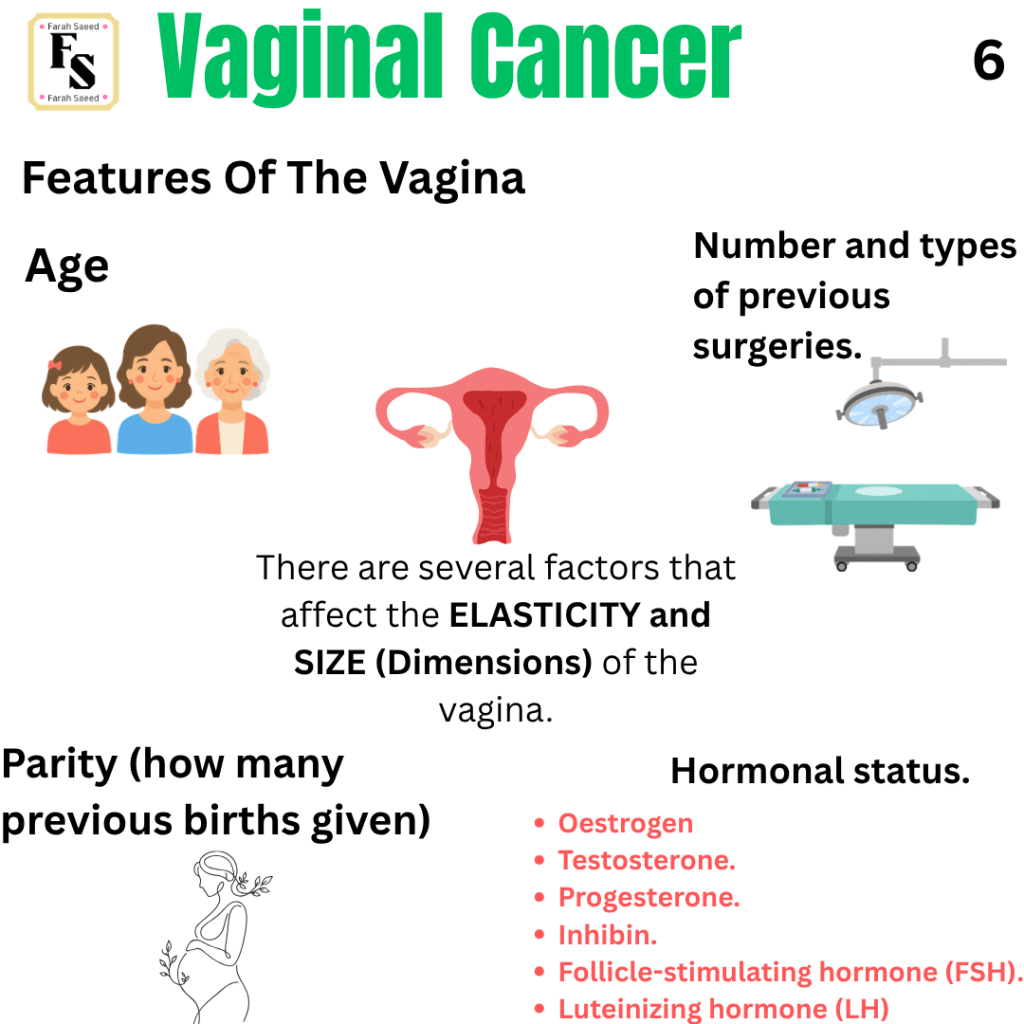
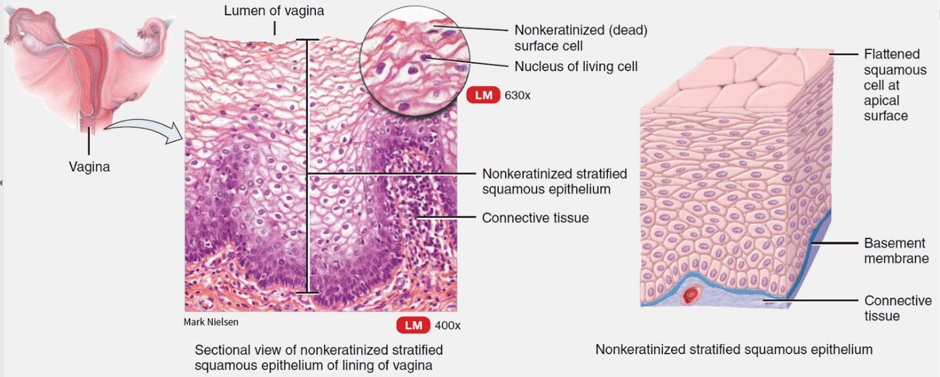
- To recap and understand the structure and function of the vagina
- To understand the types of vaginal cancer.
- To understand the causes and risk factors of vaginal cancer.
- To be aware of the signs and symptoms of vaginal cancer.
- To understand how vaginal cancer is detected.
- To understand how vaginal cancer is treated and prevented.
Polite notice: These posters are FREE to use for educational purposes and sharing across social media.
References for the following information are from the National Health Service, Cancer Research UK, Pathology Outlines, National Cancer Institute, National Institute for Health and Care Excellence, and medical research journal articles and guidelines.

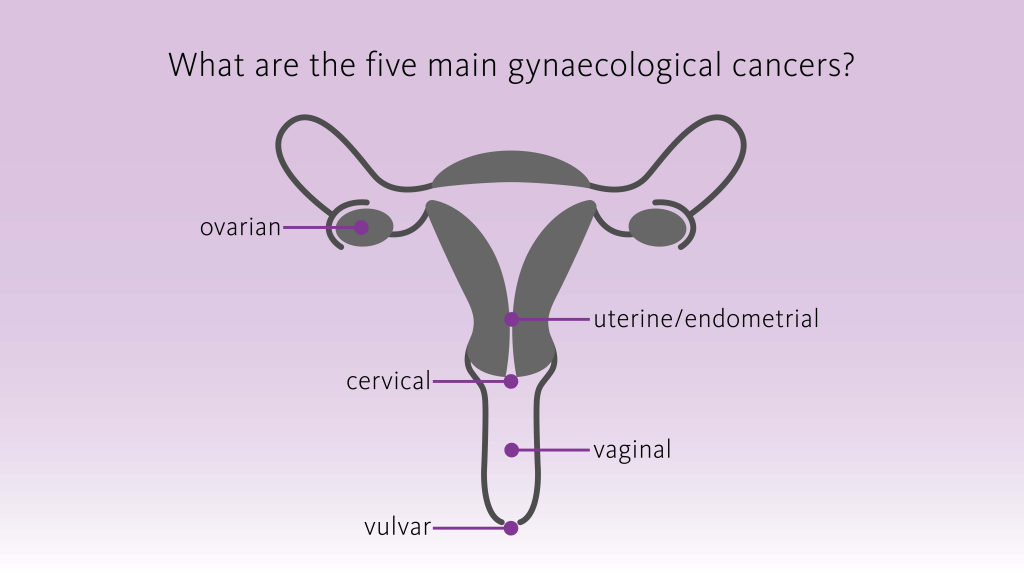
What Is Gynaecological Cancer?
Gynaecological cancers are cancers that affect the female reproductive system.
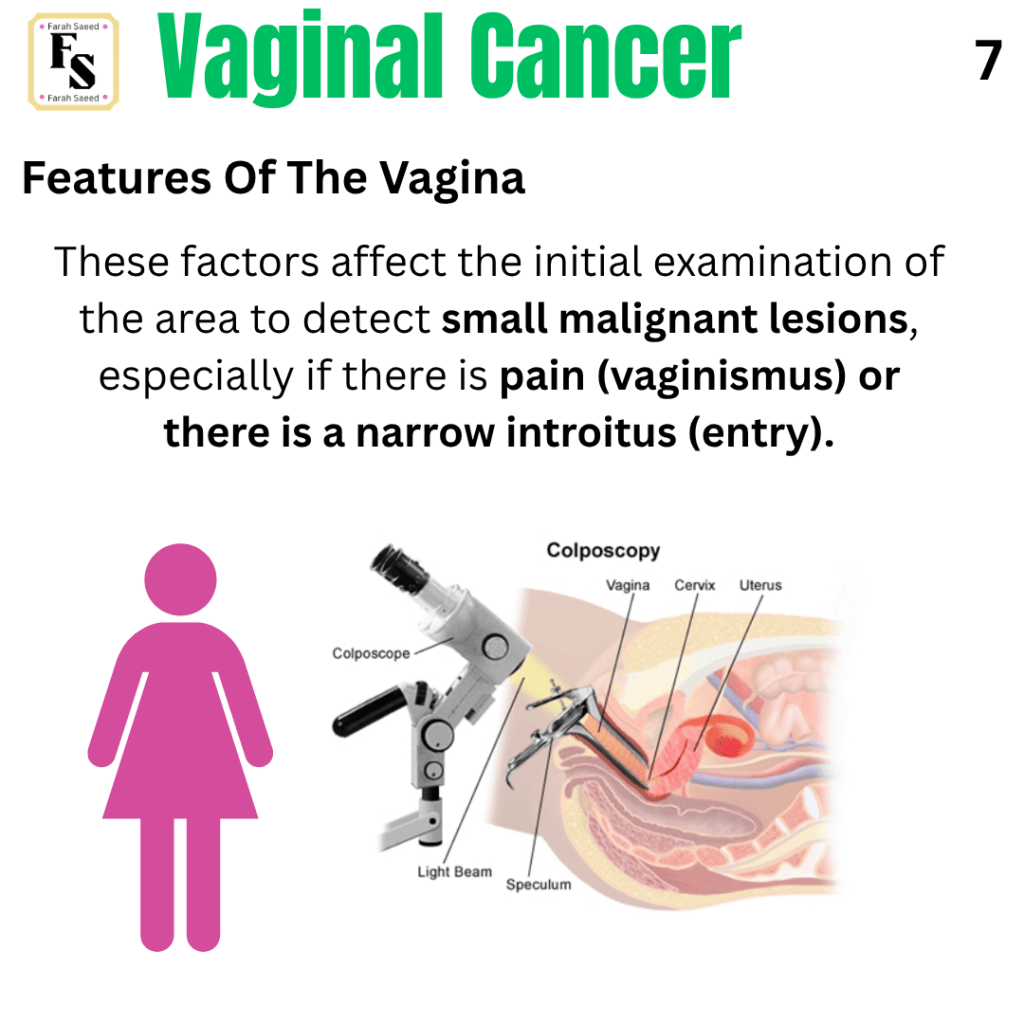
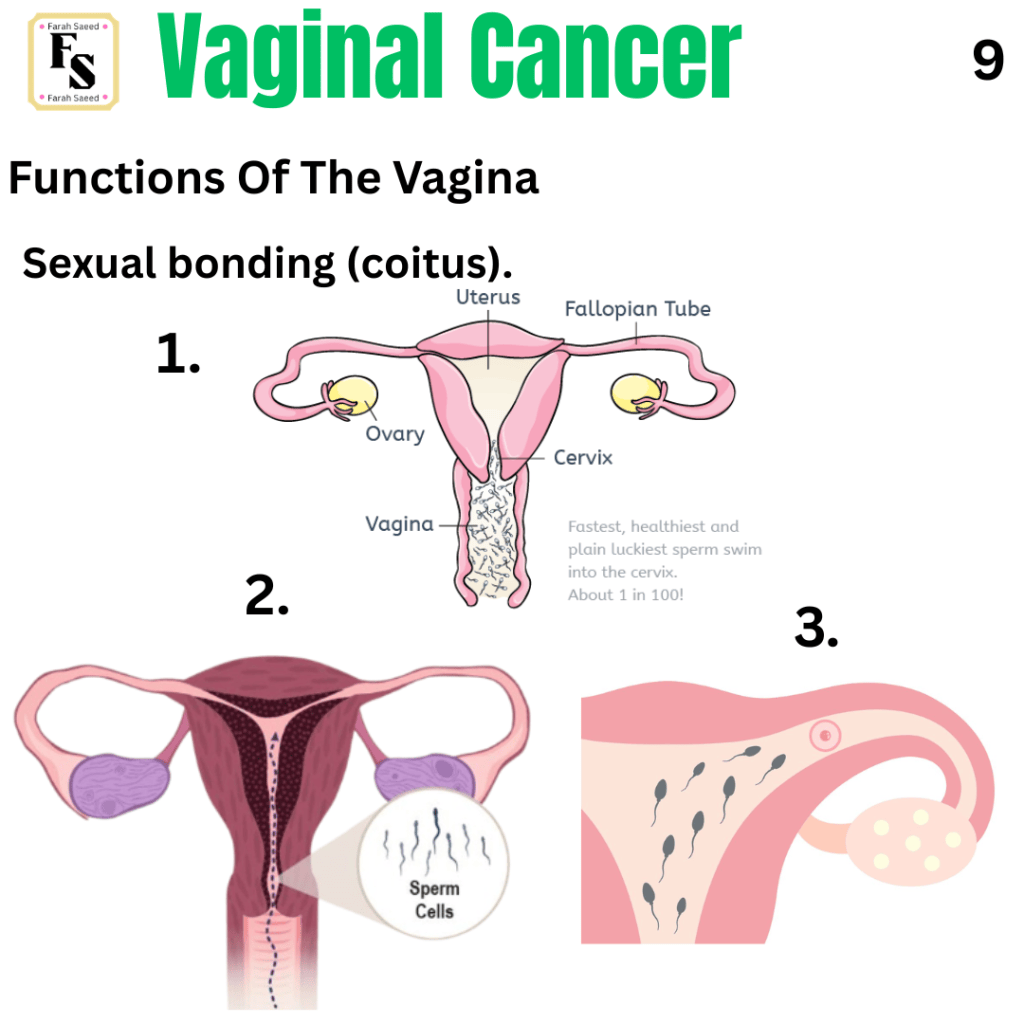
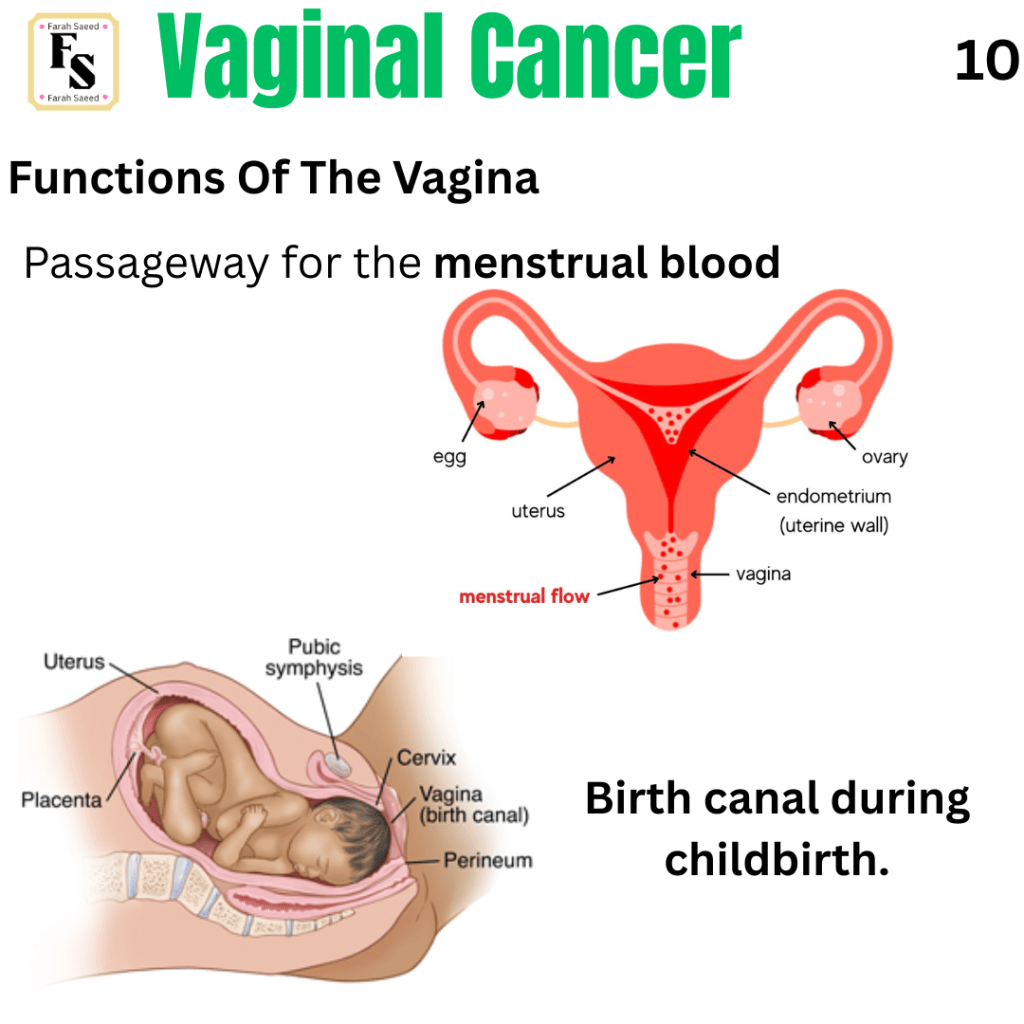
Recap: What Is The Vagina?

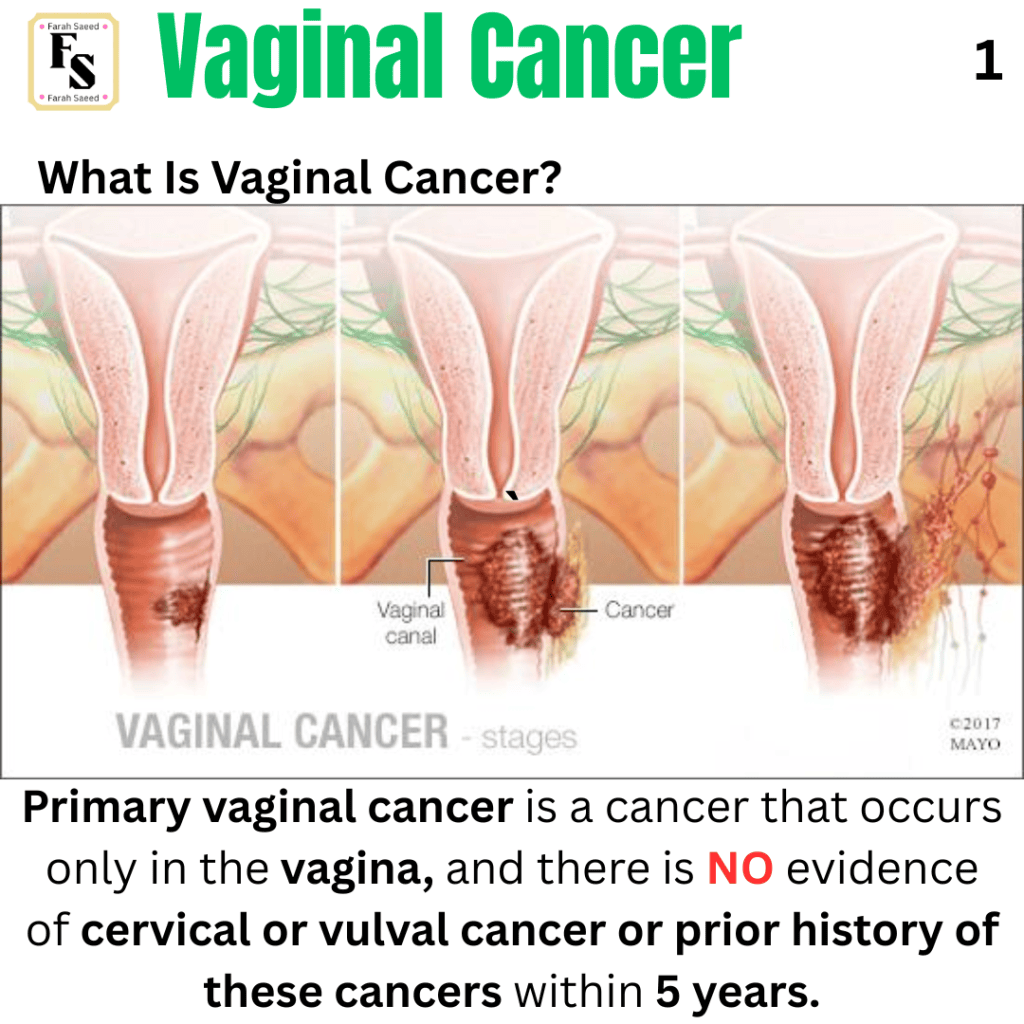
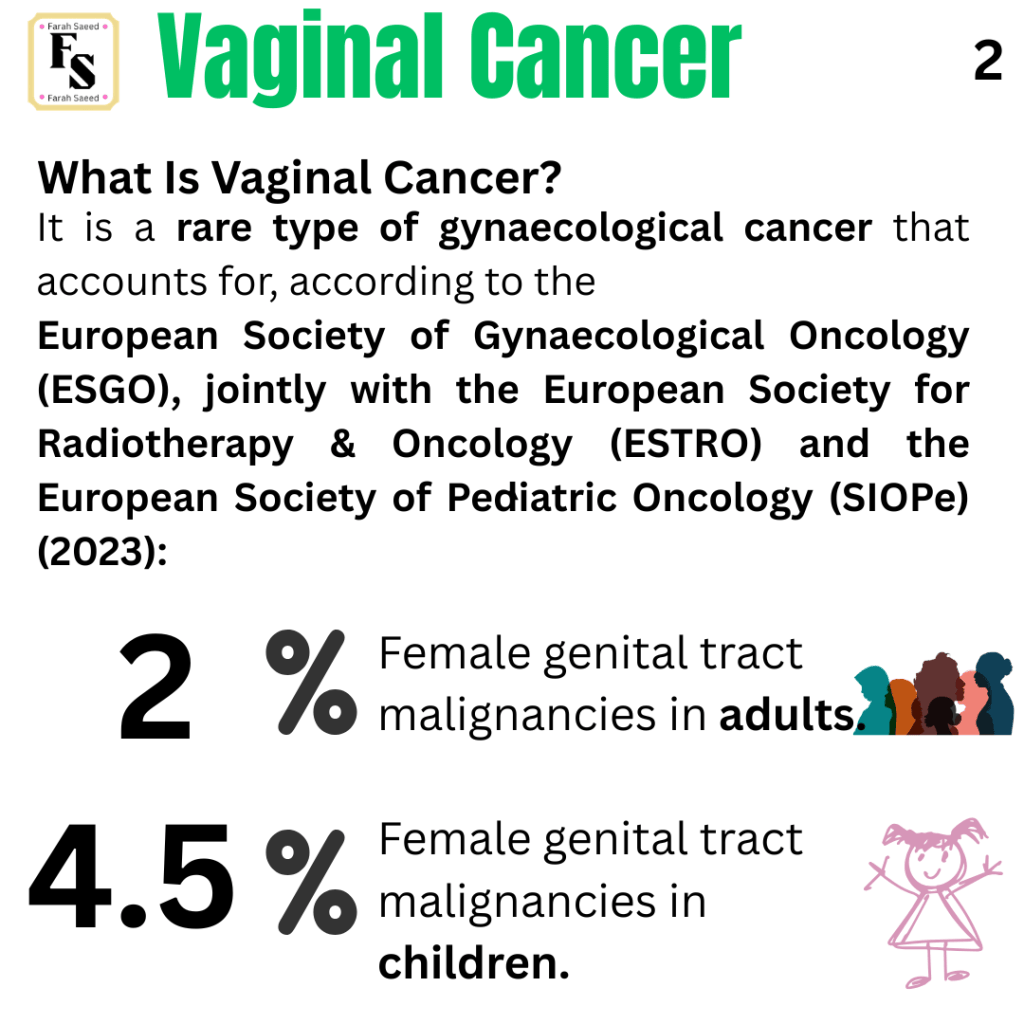
What Is Vaginal Cancer?
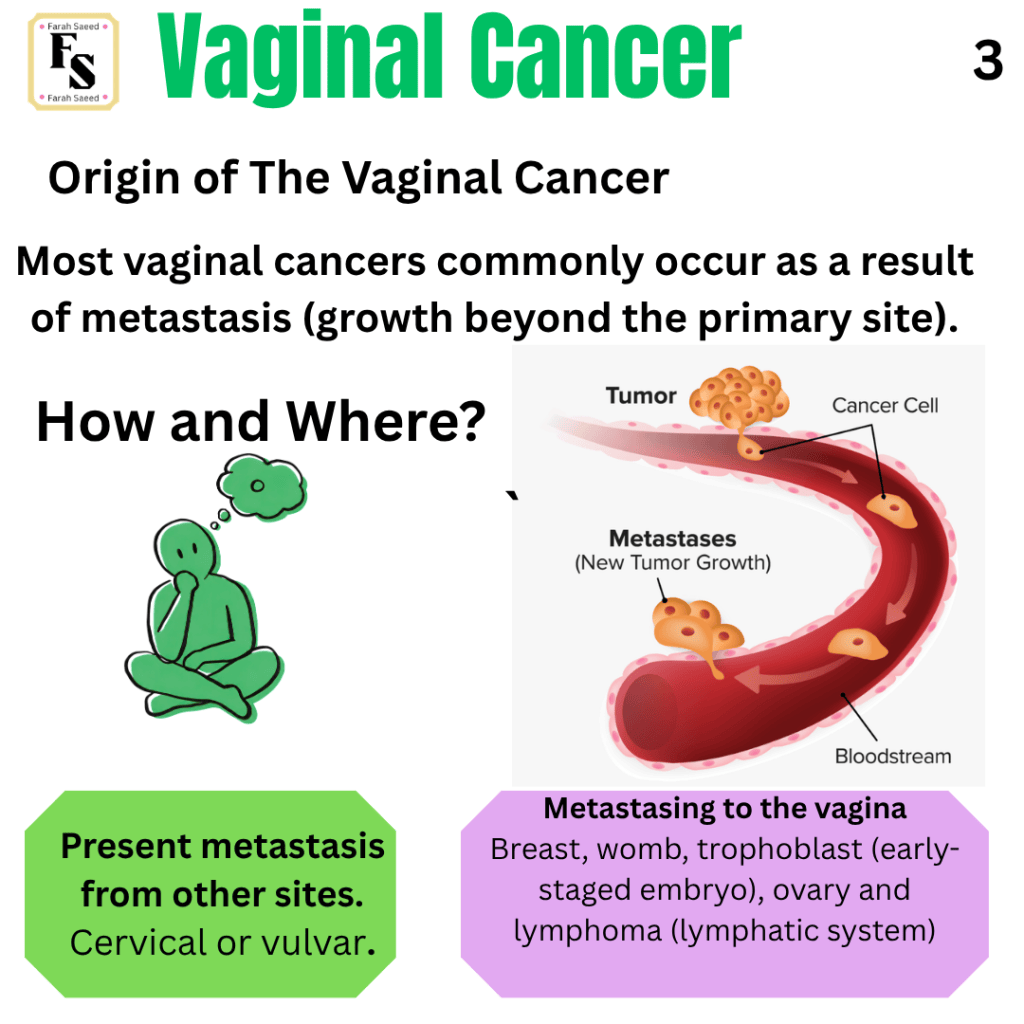
Trophoblastic cancer and its relevance to metastasis to the vagina.
Trophoblastic tumours are a rare type of cancer that arises from the trophoblast after pregnancy. There have been some cases where the trophoblastic cancers grow and can affect the vagina.
What is a trophoblast?
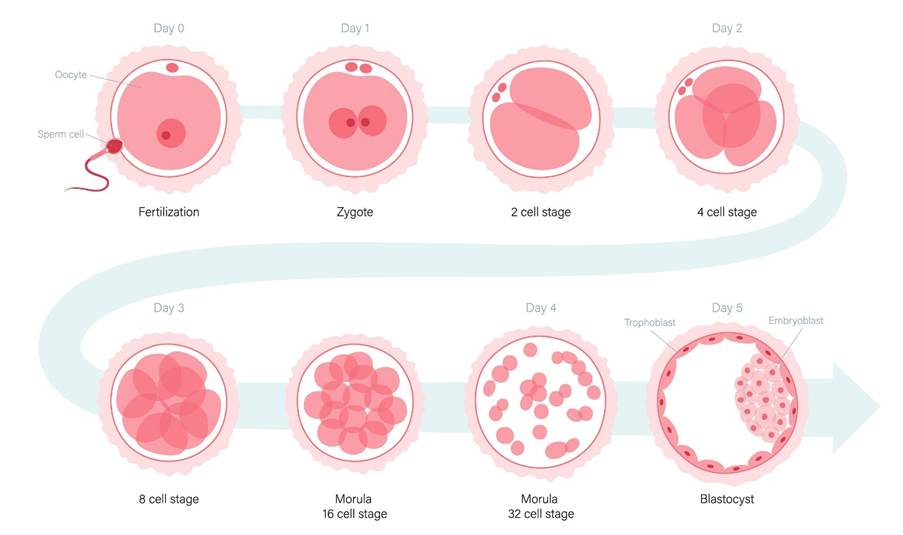
To understand what a trophoblast is, it is important to provide an insight into the development of the embryo. After the fertilization of a egg (female sex cell) with a sperm (male sex cell). A fertilized egg is the product also referred as zygote on Day 1. The zygote undergoes growth in a doubling manner: 2-cell, 4-cell on Day 2, 8-cell on Day 3 and then 16-cell (morula). On Day 4, the growing embryo becomes 32-cell (also called morula) and then on Day 5 it becomes a blastocyst where there is 32-64 cell. On Day 6, the blastocyst enters the uterine cavity with the aim of sticking onto the wall of the womb/uterus. This is referred as implantation.
The presence of the blastocyst in the uterine cavity has two outcomes on Day 8.
OUTCOME ONE:
The formation of the embryo (embryoblast). This is further subdivided into hyoblastic where there is an exocoelomic membrane called Heuser’s membrane. The hyoblast and exocoelomic membrance form the yolk sac. The other is the epiblast. The small cavity in the epiblastic is the amniotic cavity which fills with amniotic fluid. Amniotic fluid acts as a shock absorber and helps to regulate fetal temperature.
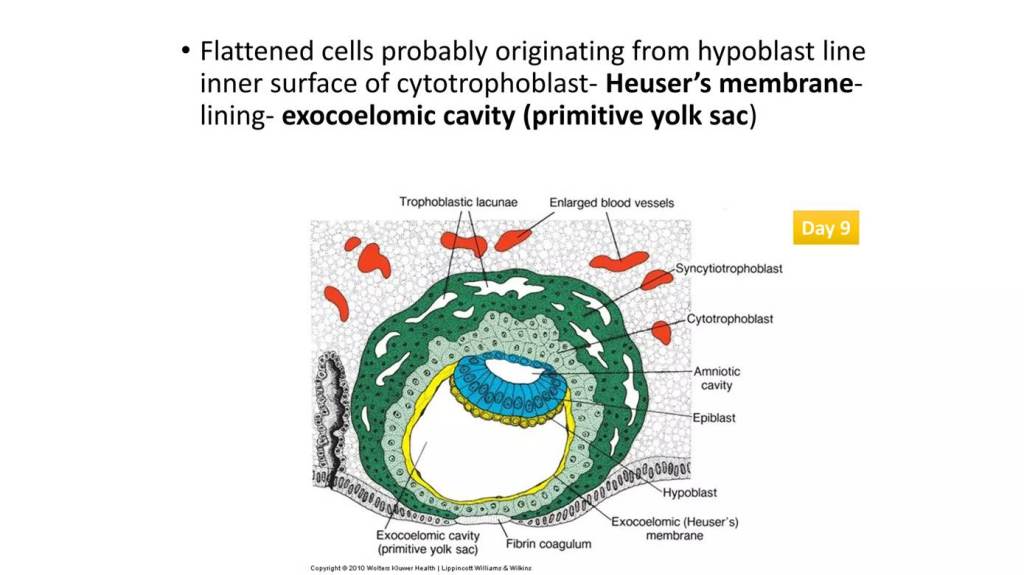
OUTCOME TWO:
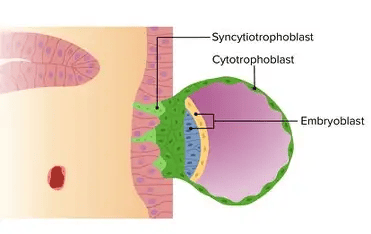
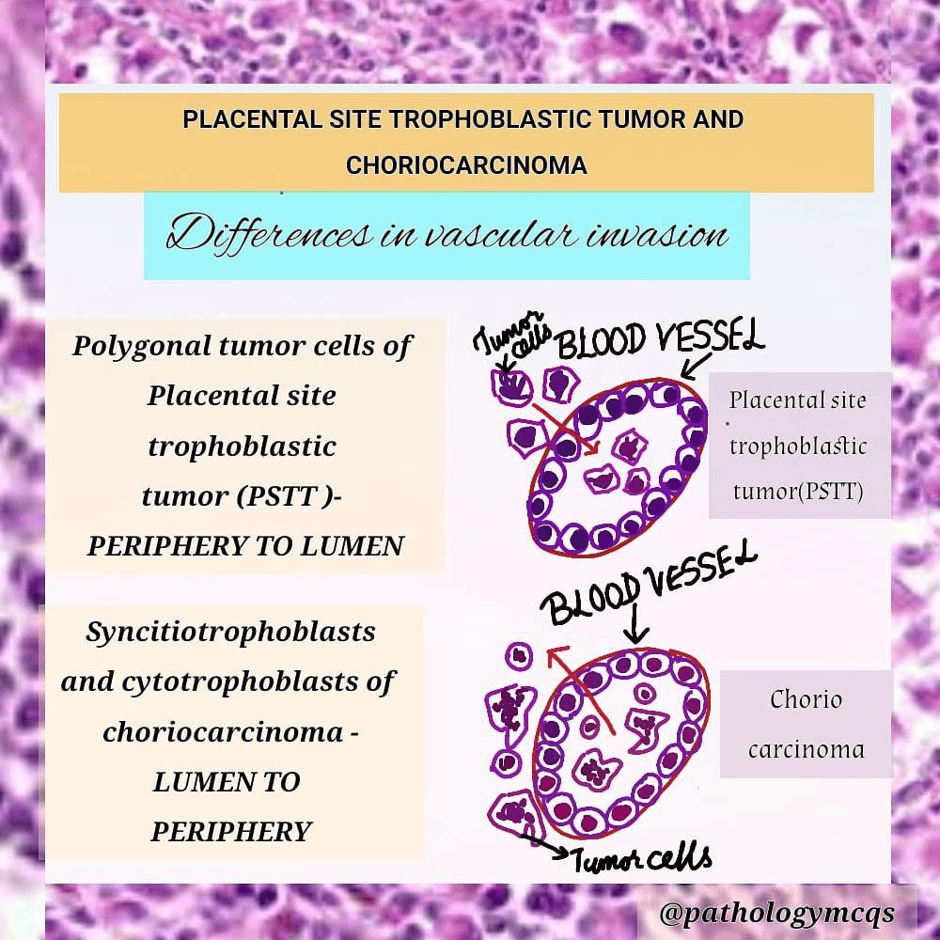
On Day 8, the outerlayer of the ball (blastocyst) forms the trophoblast. This is subdivided into syncytiotrophoblast and cytotrophoblast (inner layer). The trophoblast is what rises to form the chorionic sac.
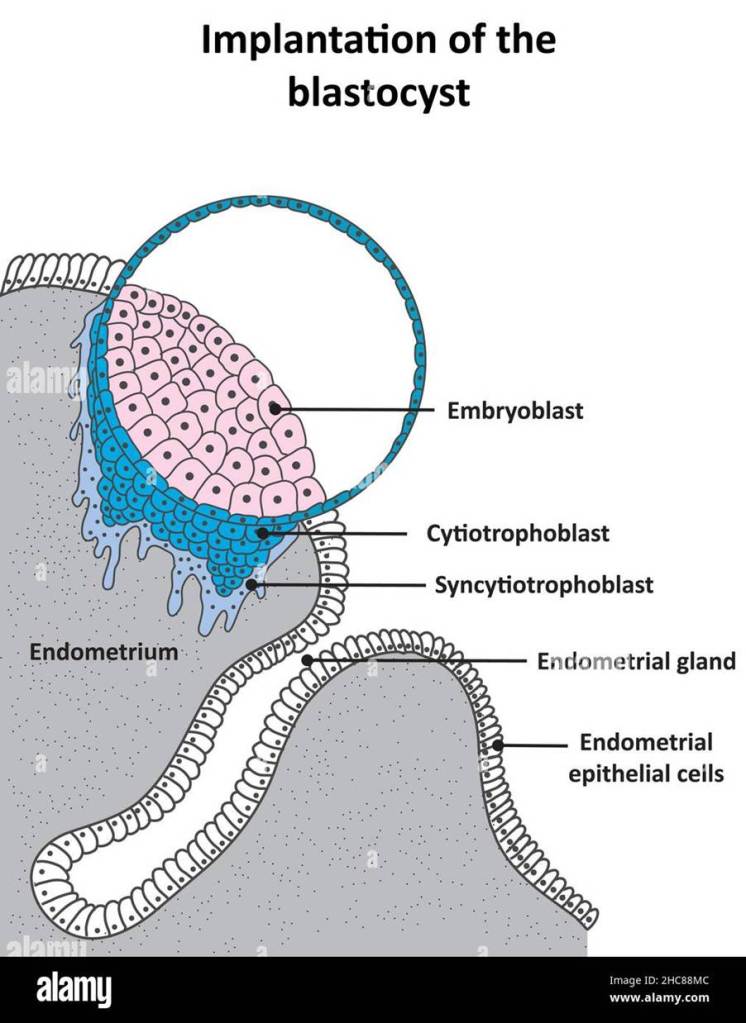
What Is the syncytiotrophoblast and cytotrophoblast?
They are cellular layers that form during implantation and help develop the chorionic villi in the placenta. The inner layer is referred to as the cytotrophoblast. This migrates outward and fuses to produce large multinucleated (lots of nuclei) syncytiotrophoblast cells. It has distinctive cell boundaries and is situated between the embryoblast and syncytiotrophoblast.
The outer layer is referred to as the syncytiotrophoblast. It helps to produce the human chorionic gonadotropin (hCG) hormone. The hCG hormone is produced by the placenta and helps to maintain progesterone levels and blocks the follicle-stimulating hormone (FSH) and luteinizing hormone (LH). This hormone also has diagnostic value, as it helps to detect pregnancy, since large amounts of it are excreted in the urine of pregnant women. It can also be detected during prenatal screening tests to detect genetic syndromes like Down’s syndrome. This hormone is also used as a tumour marker to detect very rare gynaecological cancers, for instance, malignant teratoma and endodermal sinus tumour.
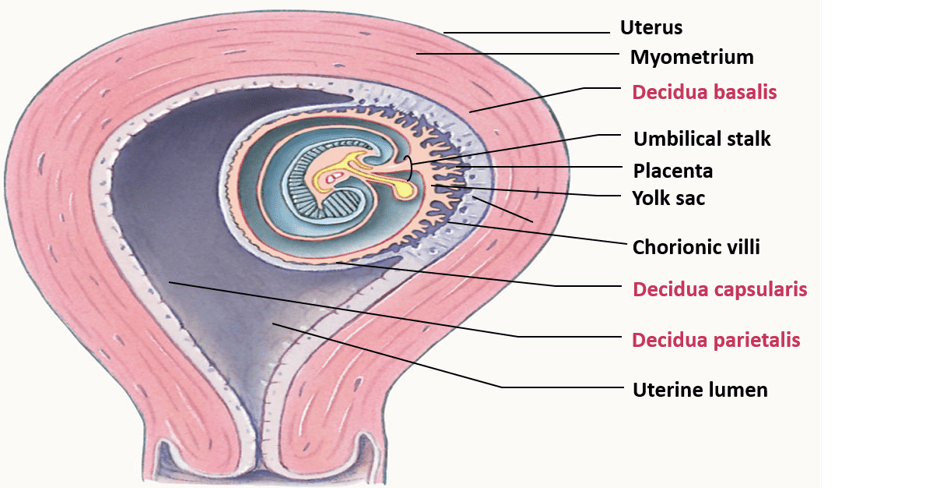
The syncytiotrophoblast helps to invade the muscle of the uterus/womb called the myometrium. This leads to the formation of new maternal blood vessels that help to provide nutrients to the growing foetus.
What happens after Day 8?
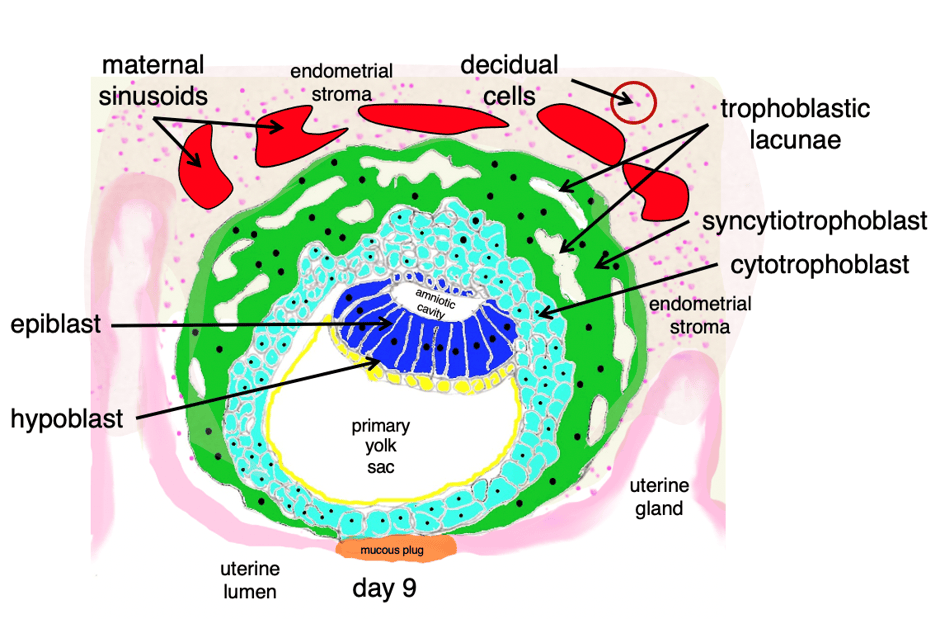
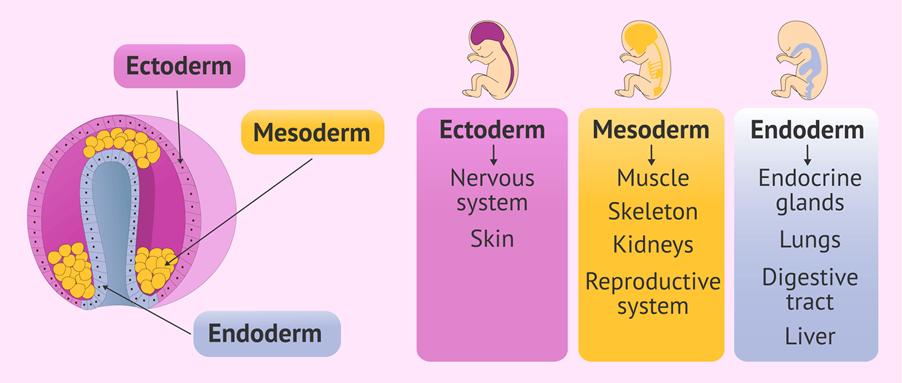
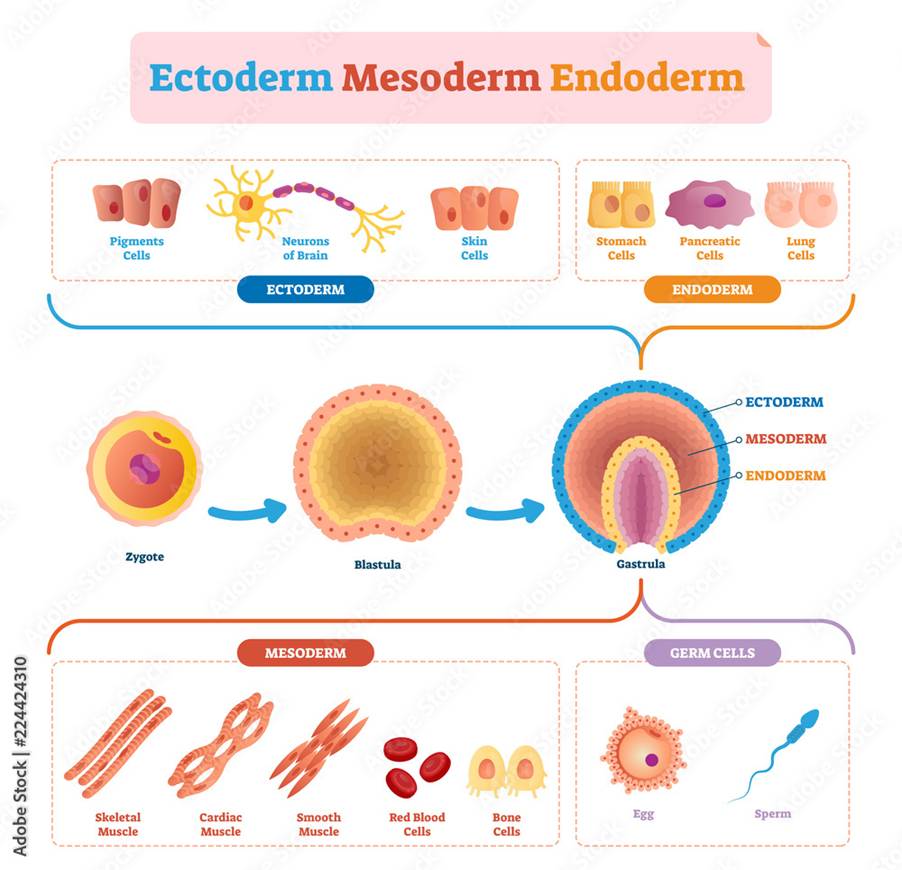
On Day 9, the blastocyst embeds in the endometrium (outer layer of the uterus). This leads to the formation of lacunae. Later on Day 15, gastrulation takes place. This is the process of forming a gastrula from a blastula. A blastula is a single-layered membrane of cells, whereas a gastrula is a double-layered structure of cells where there is a central cavity, an archenteron, that opens via the blastopore.
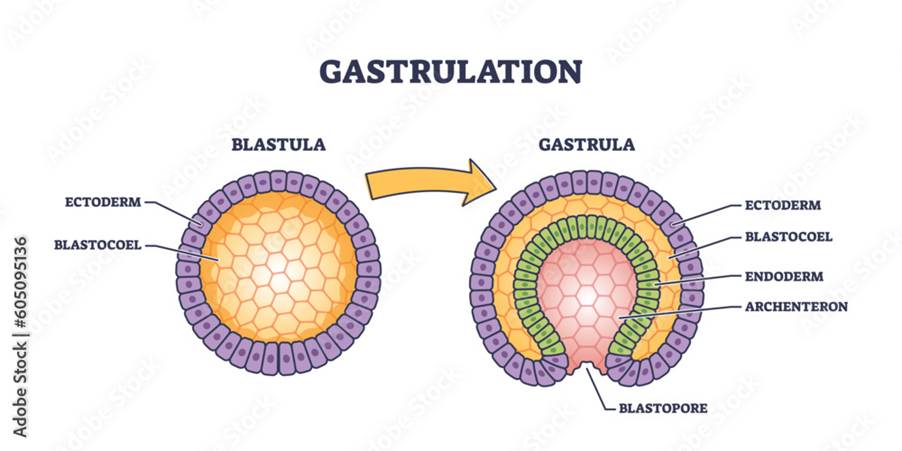
The formation of the gastrula involves several germ layers that are formed as part of embryonic development and differentiate to form particular types of body tissues. The ectoderm forms the skin (epidermis) and the nervous system. The mesoderm forms the muscles, bones, other connective tissues, kidneys, and reproductive system. The endoderm forms the gastrointestinal tract (digestive system) and the respiratory tract (breathing system), the liver, and the endocrine glands (which produce hormones).
An insight into trophoblastic tumours
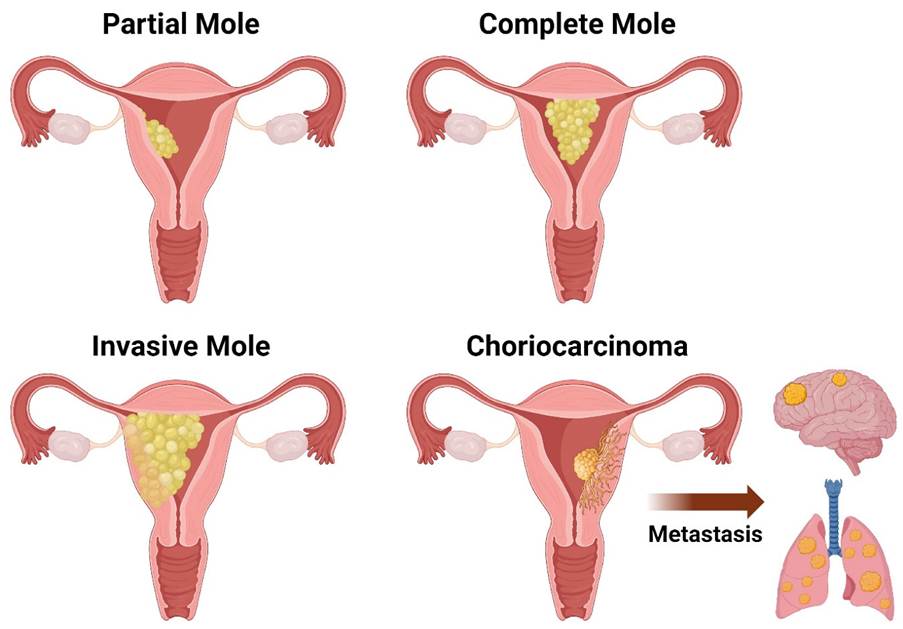
Trophoblastic tumours is commonly associated with the formation of moles or placental conditions: choriocarcinoma, highly malignant placental-site trophoblastic tumour characterised by abnormal proliferation of the placenta. Collectively, these conditions are referred to as gestational trophoblastic diseases (GTD).
The conceptus (growing embryo) is androgenic as the egg cell lacks the maternal nucleus DNA when fertilised with a sperm.
What are hydatidiform moles?
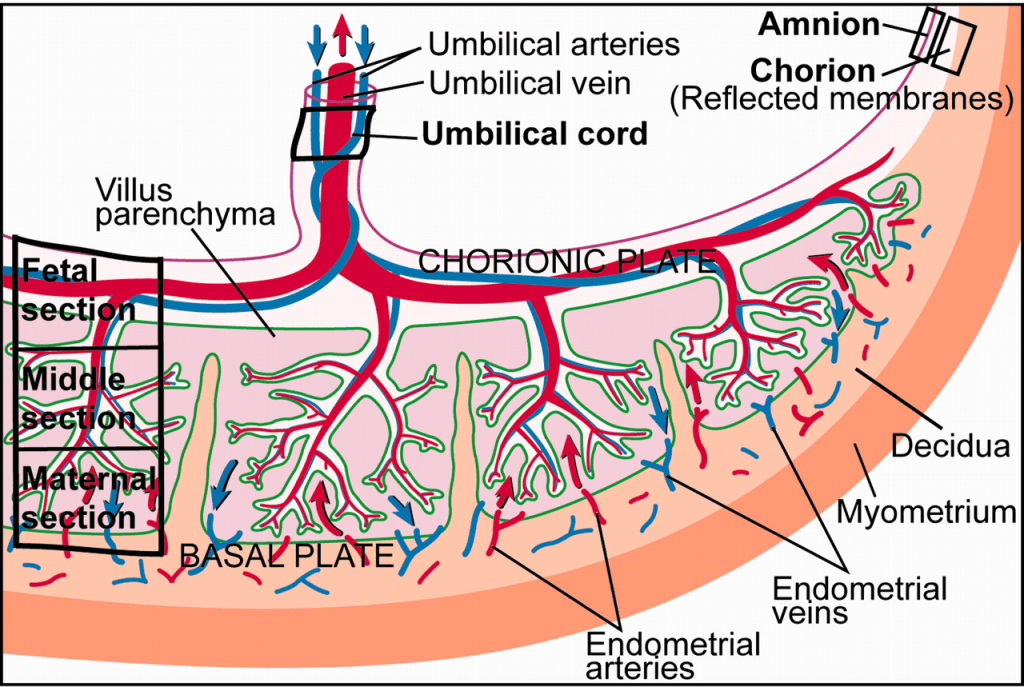
Complete hydatidiform mole (CHM) or partial hydatidiform mole (PHM) can develop from invasive moles. Hydatidiform moles are a combination of fluid-filled sacs that develop when the chorion, the membrane that surrounds the embryo, degenerates in early pregnancy with abnormal trophoblast proliferation or growth. They give a thin-walled, translucent, cystic, grape-like appearance, with swollen chorionic villi.
Chorionic villi are folds of the outer membrane that surrounds the foetus (growing baby), called the chorion. The fetal side of the placenta is formed there, where it gets its nutrients from. They also have some degree of cellular atypia. The embryo dies, the uterus enlarges, and there is a discharge of pink liquid and cysts from the vagina. On ultrasound, it has a snowstorm appearance.
What is the difference between complete and partial mole that arises in trophoblastic tumours?
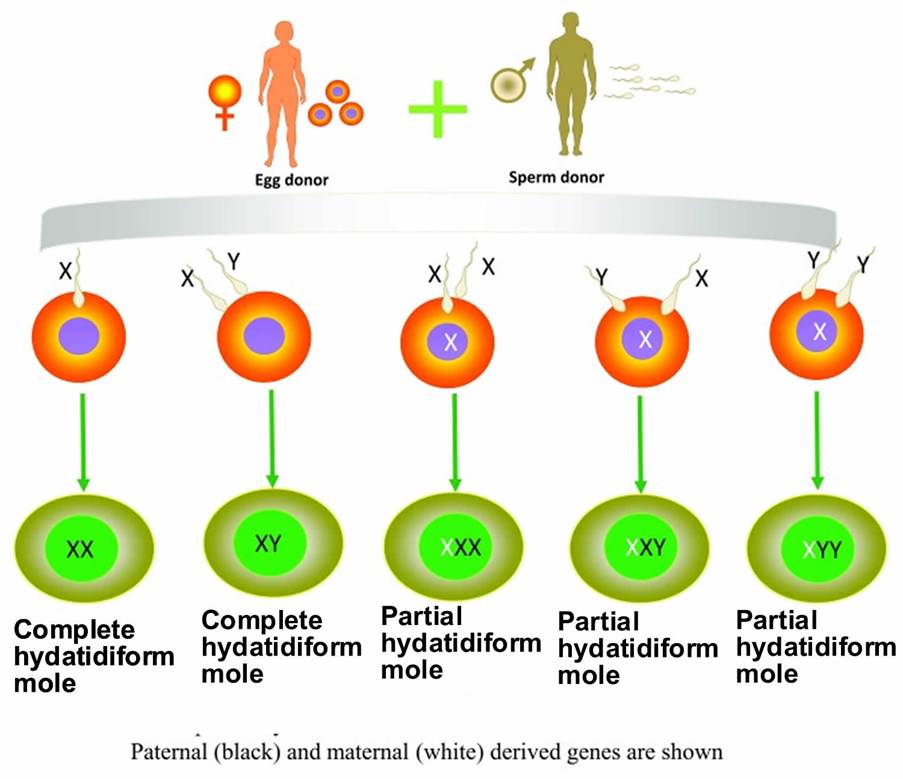
There are several difference between complete and partial mole. A complete mole occurs as a result of fertilization of an egg that lost its female chromosomes (empty egg) by a single sperm cell. This doubles the number of chromosomes, or by two sperm (dispermy). The karyotype is diploid cells that have 46 chromosomes of XX or 46, XY and are entirely paternally derived (dispermic fertilization or dispermy via father).
Generally, the male chromosome is XY and the female chromosome is XX. In comparison to body cells, the sex cells (sperm and ova) have 23 chromosomes each.
Moreover, the complete mole has mainly swollen villi, absence of fetal development, or diffuse trophoblastic hyperplasia. Diffuse trophoblastic hyperplasia is the increased production and growth of normal cells of the trophoblast, especially in the cytotrophoblast and syncytiotrophoblast.
Alternatively, a partial mole arises from fertilization of a normal egg by two sperm, leading to a triploid karyotype. There are three possible combinations: 69XXX, 69XXY, or 69 XYY. Thus, it contains both maternal and paternal chromosomes. They have some villi that are present but are hydropic (abnormal accumulation of fluid). There is fetal tissue or an embryo. It is also characterised by a specific localised growth of trophoblastic cells in the chorionic villi and thick layers of the cytotrophoblast and syncytiotrophoblast.
To differentiate from other types of hyperplasia: absence of abnormal cells (atypia), normal cell division (mitosis), no build-up of fluid in the villi (oedema), no vascular invasion in the capillaries that surround the decidua or the muscle of the uterus (myometrium), and no immature trophoblasts.
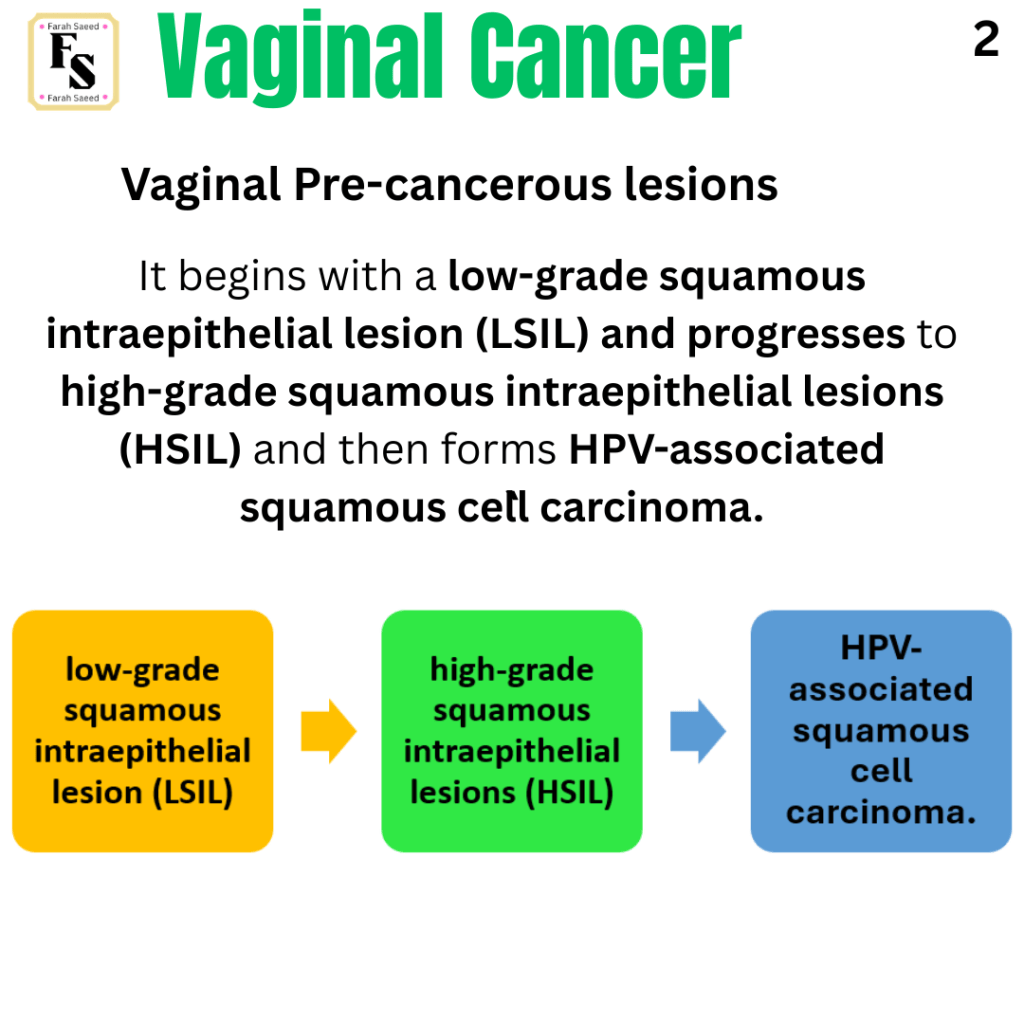
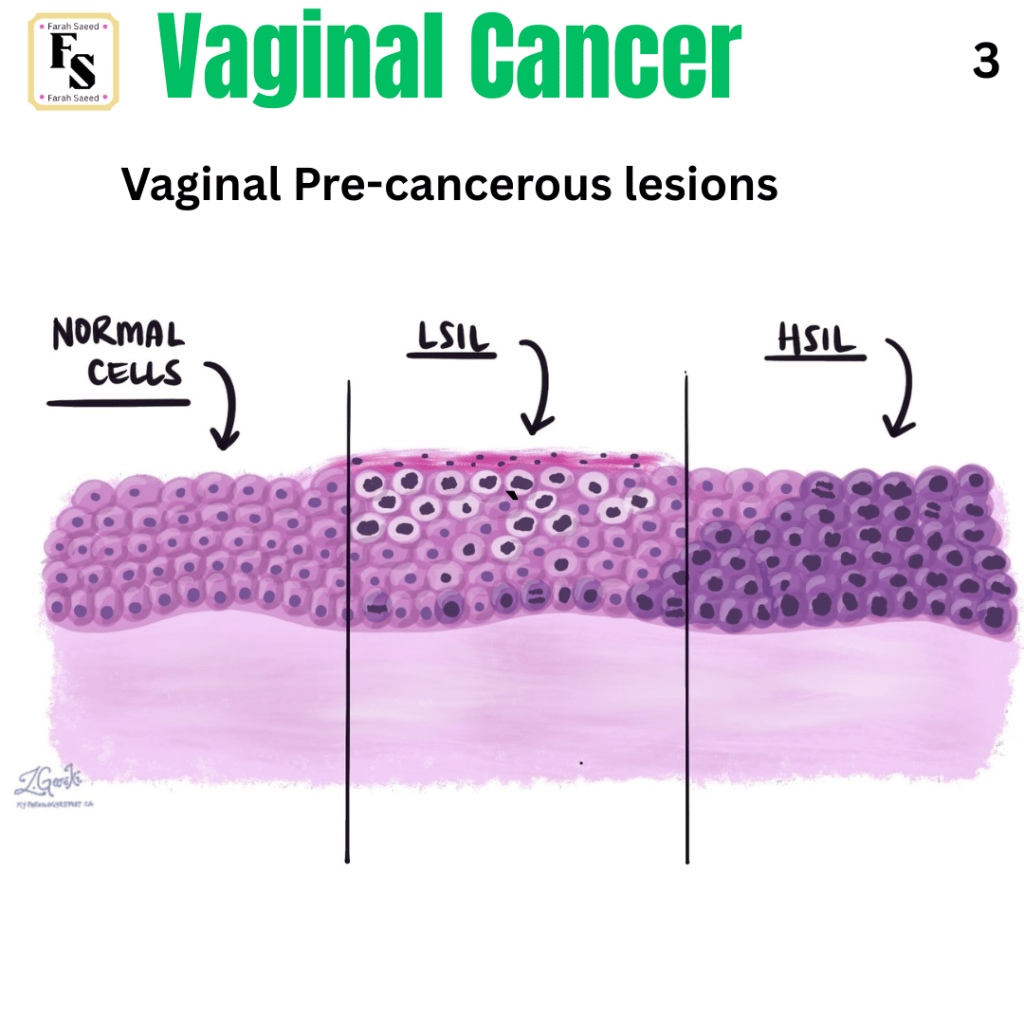
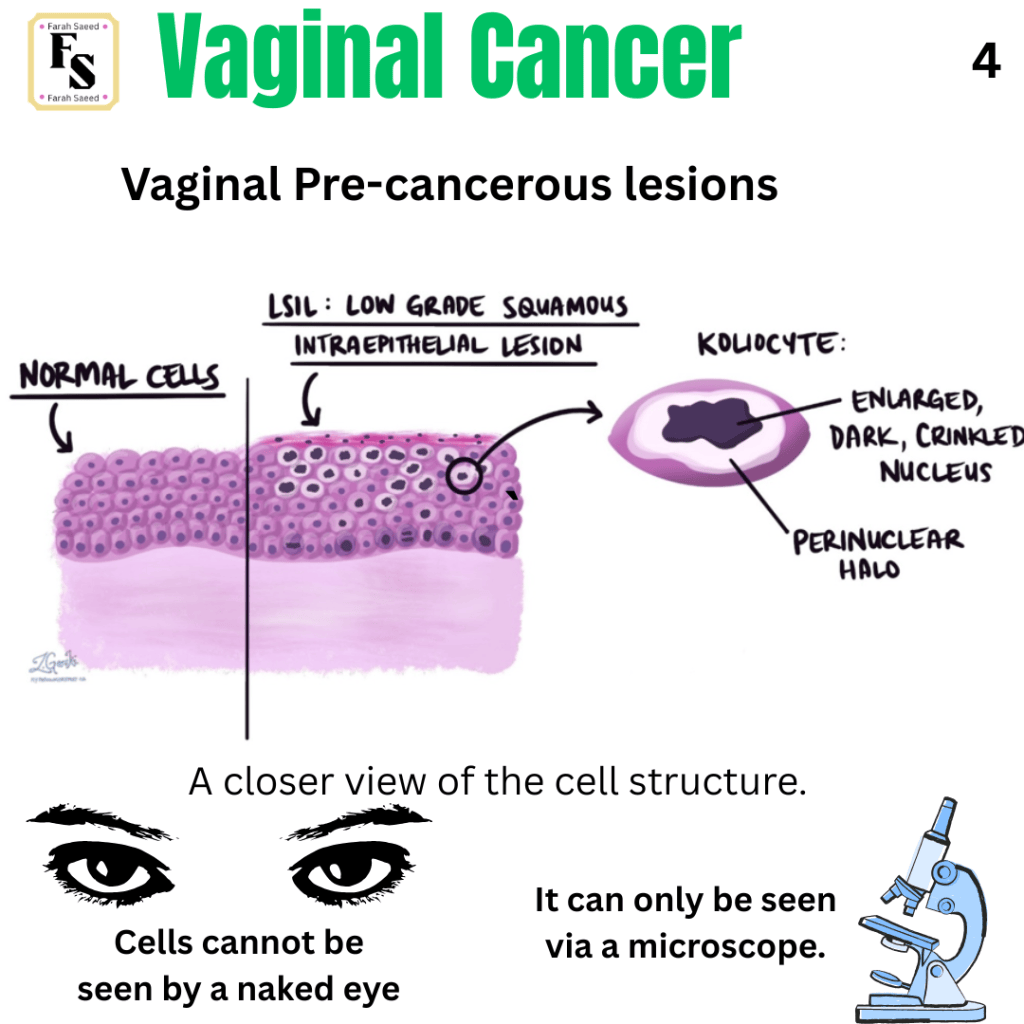
What Is A Vaginal Precancerous Lesion?

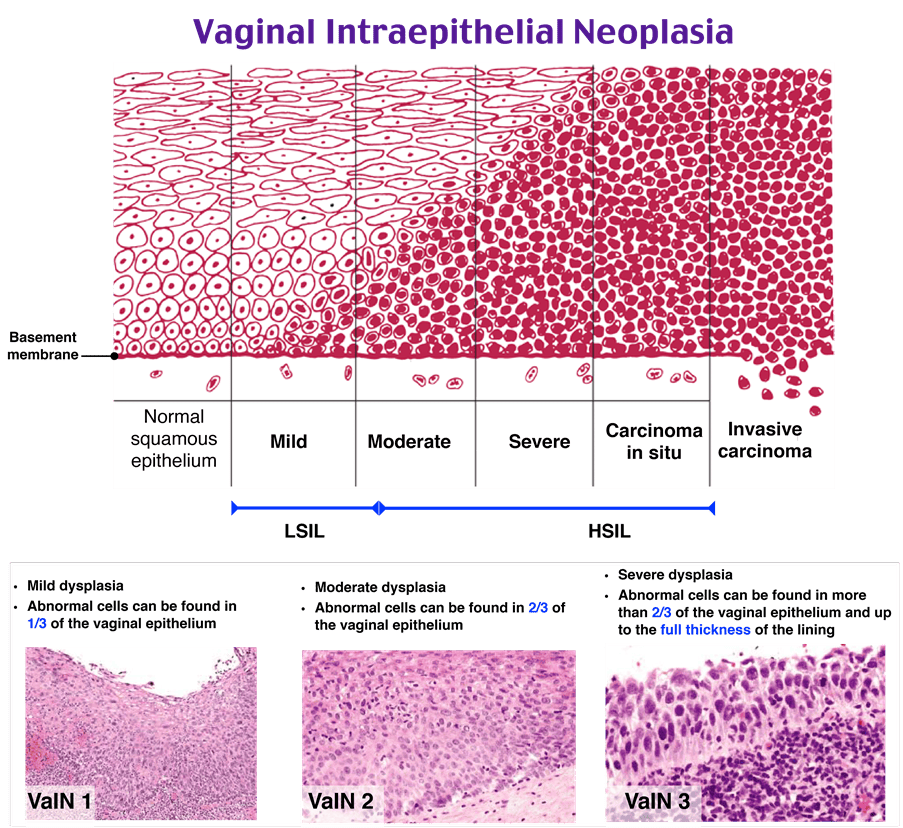
Source: Rosh Review (2026) Explanation: D is the correct answer. Available at: https://go.roshreview.com/obgyn-qid-126985 (Accessed: 16th October 2026)

References
Adams, T.S., Maluleke, J.C. and Cuello, M.A. (2025). Cancer of the vagina: 2025 Update. International Journal of Gynecology & Obstetrics, 171(S1), pp.48–59. doi:10.1002/ijgo.70325.
Cancer Research UK (2027) Vaginal intraepithelial neoplasia (VAIN) Available at: https://www.cancerresearchuk.org/about-cancer/vaginal-cancer/vain (Accessed: 11th October 2026)
Cassidy, J., Bissett, D., Spene, R. and Payne, M. (2010) Oxford Handbook of Oncology. Oxford: Oxford University Press.
Flyriver.com (2026) Focal Trophoblastic Hyperplasia: A Detailed Examination. Available at: https://www.flyriver.com/g/focal-trophoblastic-hyperplasia?auth=1792106723590 (Accessed: 16th October 2026).
Kamungo, A. (n.d.) Female Genital Tract Pathology. Available at: https://www.slideshare.net/slideshow/female-genital-tract-pathology-and-pptx/280526961 (Accessed: 11th October 2026)
National Cancer Institute (2025) HPV and Cancer. Available at: https://www.cancer.gov/about-cancer/causes-prevention/risk/infectious-agents/hpv-and-cancer (Accessed: 6th August 2026)
National Cancer Institute (2026) Vaginal Cancer Treatment (PDQ®)–Health Professional Version. Available at: https://www.cancer.gov/types/vaginal/hp/vaginal-treatment-pdq (Accessed: 17th August 2026)
National Institute of Care and excellence Gynaecological cancers – recognition and referral: Presentation. Available at: https://cks.nice.org.uk/topics/gynaecological-cancers-recognition-referral/background-information/presentation/ Accessedl 7th August 2026.
Nout, R.A., Calaminus, G., Planchamp, F., Chargari, C., Lax, S., Martelli, H., McCluggage, W.G., Morice, P., Pakiz, M., Schmid, M.P., Stunt, J., Timmermann, B., Vokuhl, C., Orbach, D. and Fotopoulou, C. (2023). ESTRO/ESGO/SIOPe Guidelines for the management of patients with vaginal cancer. International Journal of Gynecologic Cancer, [online] 33(8). doi:10.1136/ijgc-2023-004695.
Rosh Review (2026) Explanation: D is the correct answer. Available at: https://go.roshreview.com/obgyn-qid-126985 (Accessed: 16th October 2026)
Shankar, V. (2024) Gestational Trophoblastic Diseases: Part 1: Complete and Partial Hydatidiform Moles. Available at: https://ilovepathology.com/gestational-trophoblastic-diseases-part-1-complete-and-partial-hydatidiform-moles/ (Accessed: 16th October 2026)
The Eve Appeal (2026) Vaginal Cancer. Available at: https://eveappeal.org.uk/information-and-advice/gynaecological-cancers/vaginal-cancer/ (Accessed: 7th August 2026)
Updated October 2026; Next Review September 2028


Leave a Reply